When poor head control may be more than a lack of practice
Recently, I began working with a four-and-a-half-month-old baby whose family had been concerned about development for more than two months. Both the parents and grandparents had noticed that the baby’s head control did not appear to be progressing as expected. They raised their concerns during pediatric visits, but they were reassured that everything was fine. Their concern did not disappear after reassurance. Eventually, the parents searched online for a pediatric physical therapist and found me.
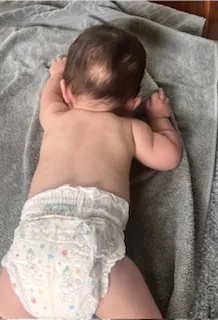
During my evaluation, it was clear that their observations were meaningful. At four and a half months, the baby had very limited head control and low muscle tone throughout the body. The difficulty was not confined to one position or one activity. It affected the baby’s ability to organize the head and trunk against gravity, tolerate tummy time, and begin developing the postural control needed for supported sitting and later motor skills.
This family’s experience raises an important issue. Parents don’t need to know medical terminology to understand what they see. They may not say their baby has low muscle tone, reduced antigravity control, or delayed postural development. But parents observe their baby daily and often notice small signs before they become obvious. Signs they could miss during a brief medical visit. When a parent repeatedly says, “Something does not seem right,” that concern deserves careful attention.
What Should Head Control Look Like at Four Months?
Head control develops gradually during the early months of life. A newborn’s head needs support because the neck and trunk muscles cannot yet maintain alignment against gravity. With growth, experience, and repeated opportunities to move, babies begin lifting and turning their heads, holding the head more steadily when carried, and pushing up during tummy time.
By about four months, most babies develop much more consistent head control. When held upright with appropriate support around the body, the head should remain relatively steady rather than falling backward, forward, or repeatedly to the side. During tummy time, a baby will usually begin lifting the head and upper chest while bearing weight through the forearms. The baby may turn to look toward a parent, a voice, or an interesting toy. Some babies reach a skill earlier, while others need more time or more opportunities to practice.
What matters is the overall pattern. Is head control gradually becoming steadier? Is the baby beginning to work against gravity? Are tummy time skills progressing? Does the baby move both sides of the body? Is the baby becoming more active, more organized, and more capable over time? When there is little progress, the head remains difficult to control, or the baby appears unusually floppy or weak, it is appropriate to look more closely. Waiting because every baby develops at a different pace can delay support when development differs meaningfully.
When Poor Head Control May Be More Than a Lack of Practice
Babies need opportunities to move. A baby who spends little awake time on the floor may have fewer chances to practice lifting the head, pushing through the arms, reaching, kicking, rolling, and shifting weight. Limited tummy time can affect strength, endurance, and familiarity with movement in prone. More floor time may be an important part of the plan. However, not every difficulty can be explained by a lack of practice.
I was asked whether the delay might be related to frequent holding and not moving enough. It was a reasonable question. The amount and quality of a baby’s movement experience are always worth considering. My answer was that this baby’s presentation was not explained by limited floor time. The baby showed generalized low muscle tone and developmental delay. Reduced movement opportunities could make the delay more noticeable or limit strength building, but being held did not explain the low tone I observed throughout the body. Practice can improve skill, strength, endurance, and confidence. It does not change the fact that some babies begin movement with a different level of muscle tone or postural control and may require more individualized support.
I never want a parent to feel blamed for holding a baby. Babies need to be held. Holding supports attachment, communication, regulation, feeding, and emotional security. The question isn’t whether parents have held their baby too much, but whether the baby also has regular, safe opportunities to move freely in different positions while awake.
Understanding Low Muscle Tone in Babies
Muscle tone refers to the resting level of tension in the muscles and the resistance the body provides during movement. Low muscle tone, or hypotonia, is not the same as muscle weakness, although the two can occur together. A baby with low tone may feel softer or less stable when held and may need to work harder to maintain the head, trunk, or limbs against gravity.
Low tone can affect movement in different ways. Some babies have difficulty maintaining a tucked, organized position and appear to spread out against the supporting surface. Some have trouble bringing their hands toward the middle of the body or lifting their legs. Others may have difficulty sustaining head lifting during tummy time, stabilizing the shoulders, or maintaining an upright position even with support.
A baby with low tone may still move actively and engage socially. Smiling, looking toward a parent, vocalizing, or reaching for a toy does not rule out a motor concern. Development includes many areas, and a baby can show strengths in one area while needing support in another.
Many possible reasons can cause a baby to demonstrate low tone, and the cause may not be immediately clear. A physical therapist does not determine every underlying medical cause. Our role includes identifying the movement findings, documenting their effect on development, beginning appropriate intervention, and communicating with the baby’s medical team when additional evaluation may be warranted. Working together, the family and health care team can determine whether developmental follow-up or assessment by another specialist is appropriate.
Parents Often Notice the Small Signs First
Parents see their baby in ways no professional can during a short appointment. They observe how the baby wakes, feeds, moves during diaper changes, responds to being carried, tolerates the floor, and settles to sleep. They notice whether head control changes week to week and whether one side of the body is used differently.
Parental concern is not a diagnosis, but it is valuable developmental information. When parents repeatedly express the same concern, the response should go beyond reassurance. What exactly are they observing? When does it happen? Is the pattern changing? Can they share a short video from home? Would a standardized developmental screen or referral provide more information? An assessment may confirm that a baby is developing within an expected range. Sometimes the assessment identifies a delay or movement pattern that would benefit from early support. Either outcome is better than leaving a family with an unaddressed concern.
Reassurance Should Follow Observation
Parents deserve reassurance when appropriate. The early months can feel overwhelming, especially when families are surrounded by milestone charts, comparison, and conflicting advice online. Not every variation is a warning sign, and not every baby who dislikes tummy time has a developmental delay. At the same time, “wait and see” should not be the response to a persistent concern. Reassurance is most meaningful when it follows careful observation and a thoughtful discussion of what the baby is doing now, what progress should follow, and when the family should return if progress does not occur. Referring a baby for an evaluation does not mean assuming the worst. It means gathering information. A useful plan might be: “I see the difficulty you are describing. Let’s look at how your baby controls the head in several positions. Here are two strategies to try at home, and I want to reassess in two weeks.” If the concern is more significant, a referral to pediatric physical therapy or another provider can offer additional information without waiting for the delay to become more pronounced.
Why a Medical Visit May Not Show the Whole Picture
Well-child visits cover a lot of information. Pediatricians assess growth, feeding, sleep, health, safety, immunizations, family concerns, and development, often within a limited appointment. A baby may move differently in an unfamiliar environment than at home.
Some movement difficulties are obvious immediately. Others become clearer when observed in several positions and given time to attempt a task. A pediatric physical therapy evaluation may include observation in supine, side-lying, prone, supported sitting, and upright carrying. We look at alignment, symmetry, muscle tone, strength, range of motion, postural reactions, movement variety, endurance, and the strategies the baby uses to accomplish a task.
We also want to know how the baby responds after repeated attempts. Can the baby lift the head briefly but not sustain it? Does the baby fatigue quickly? Is the movement easier to one side? Does support at the shoulders or trunk change the baby’s ability? These details help distinguish an emerging skill from a broader postural control difficulty. Standardized developmental measures can add useful information, but observation remains essential. A score can tell us how a baby compares with an expected developmental range. It does not always explain why the movement is difficult or which supports will help the baby succeed.
What Early Pediatric Physical Therapy Can Address
When I began working with this baby twice a week, our immediate goals included improving head control, increasing tolerance for tummy time, developing antigravity strength, and supporting greater organization of the head and trunk. I also taught the family how to position and handle the baby in ways that encouraged active participation throughout the day.
Infant therapy should not look like an adult exercise program. Babies learn through movement, play, touch, visual engagement, repetition, and interaction with caregivers. A therapist may adjust the tummy time angle, support the shoulders or chest, help the baby shift weight, encourage reaching toward a parent, or use carrying positions that activate the neck and trunk without overwhelming the baby.
The home program must be realistic. Families do not need to turn every interaction into therapy. They can incorporate small opportunities into existing routines, such as diaper changes, floor play, carrying, and transitions between positions. The goal is to help the baby experience successful movement frequently enough for change to occur.
Since beginning therapy, this baby has made significant progress. Head control is improving. Tummy time is becoming more active and better tolerated. Supported sitting is more organized, and the baby is showing greater ability to engage the muscles needed to work against gravity. Progress does not mean the family’s original concern was unnecessary. It confirms the baby can change with the right support, repetition, and opportunities to move.
Early Support Is Not the Same as Rushing Development
Some parents hesitate to seek therapy because they do not want to pressure their baby or force milestones. That is understandable. Pediatric physical therapy should not aim to make every baby reach milestones as quickly as possible. Early intervention improves the quality and variety of movement, helps a baby access positions that support development, and prevents one limited strategy from becoming the only strategy. It can also reduce frustration for both the baby and the family. There is a difference between allowing normal developmental variation and overlooking a significant lack of progress. A baby gradually gaining head control may simply need continued floor time and monitoring. A baby with very limited head control, generalized low tone, and difficulty working against gravity at four and a half months presents a different picture. An evaluation helps explain that difference.
When Should Parents Ask for Another Opinion?
Parents should feel comfortable asking more questions when their concern persists, a skill isn’t progressing, or their baby’s movement looks consistently different from what they expected. A second opinion may be especially helpful when a baby has difficulty controlling the head, feels unusually floppy or stiff, strongly favors one side, has limited movement variety, struggles to tolerate tummy time despite gradual practice, or loses a previously present skill.
Parents can bring specific observations to an appointment. Instead of saying, “I am worried about my baby’s development,” try being more specific: “My baby’s head still falls backward every time I bring the baby toward sitting,” or, “During tummy time, my baby cannot lift the head and becomes exhausted quickly.” A short video taken at home can also help demonstrate a pattern that may not appear during the visit. Consider asking, “What would you expect to see over the next few weeks?” “When should we follow up?” “Would a developmental screening be helpful?” or “Can we have a referral for a pediatric physical therapy evaluation?” Seeking another opinion is not a rejection of a trusted pediatrician. Health care works best when professionals and families share information and remain open to another perspective when questions continue.
Parents Are Their Baby’s Best Advocates
Parents do not need to diagnose their babies. However, it is appropriate to keep asking questions when something does not feel right. In this family’s case, the parents and grandparents noticed an early difference. They kept expressing concern and found a pediatric physical therapist. Their advocacy led to closer evaluation and earlier support.
Sometimes an evaluation provides reassurance and a few practical ideas. At other times, it identifies a need for therapy or further medical assessment. Either way, listening creates the opportunity to respond appropriately. Reassurance is valuable when it follows careful observation. When concerns continue, seeking another opinion is not overreacting. It is advocacy.
If you are concerned about your baby’s head control, muscle tone, tummy time, symmetry, or early motor development, you do not have to wait until the difference becomes more obvious. An evaluation can clarify what you are seeing, identify your baby’s strengths, and determine whether additional support would help.
About the Author
Dr. Tara Losquadro Liddle, PT, DPT, PCS, is a board-certified pediatric clinical specialist with more than 30 years of experience working with infants and children. She founded Motor Skills Matter™ and wrote Why Motor Skills Matter: Improve Your Child’s Physical Development to Enhance Learning and Self-Esteem.